
7 Hormonal Factors That Could Explain Stubborn Weight Gain

You’ve changed your diet, cut back on calories, and made a real effort to lose weight. Perhaps it worked for a while. Then the progress stopped, the pounds crept back, or your waistline started changing despite doing everything you thought was right.
The usual advice is predictable: eat less, move more, and be consistent. But what happens when you’ve already tried all three?
Weight loss is often presented as a straightforward calculation. Yet the human body isn’t a calculator. It constantly adjusts to changes in food intake, sleep, stress, and reproductive health, sometimes in ways that make losing weight unexpectedly difficult.
And here’s the question worth investigating: could the very changes you’re making to lose weight be triggering biological responses that make it harder?
Research has uncovered some surprising answers, including why certain blood tests can miss early metabolic problems, why repeated dieting can intensify hunger, and why women’s bodies can change significantly during midlife without a dramatic shift on the scale.
Let’s examine seven hormonal factors that may help explain what’s happening beneath the surface—and what the science actually tells us about them.
Disclosure: The information provided is for educational purposes only and not intended as medical advice. Consult a healthcare professional before making any changes to your health routine.
- 7 Hormonal Factors That Could Explain Stubborn Weight Gain
- 1. Insulin Resistance: When Normal Blood Sugar Hides a Problem
- 2. Thyroid Hormones: When Your Metabolism Slows Down
- 3. Cortisol: How Chronic Stress Changes Your Body
- 4. Leptin Resistance: When Your Brain Stops Listening
- 5. Estrogen: Why Weight Changes During Perimenopause
- 6. Testosterone: When Hormonal Imbalances Affect Weight
- 7. Ghrelin: Why Weight Loss Makes You Hungrier
- Gaining Weight Despite Normal Blood Tests?
- Final Thoughts: When Weight Gain Is More Than Calories
1. Insulin Resistance: When Normal Blood Sugar Hides a Problem
You’ve been gaining weight, particularly around your stomach. You’re watching what you eat, but the weight isn’t coming off. Your doctor checks your blood sugar, tells you everything looks normal, and sends you home.
But there’s something important you may not have been told.
Your blood sugar can be normal even when you’re insulin resistant.
Here’s how it works.
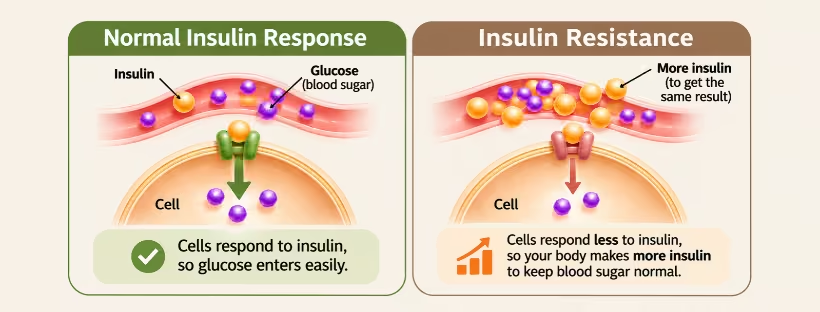
When you eat carbohydrates, your digestive system breaks them down into glucose (sugar), which enters your bloodstream. Your body needs that glucose for energy, but first it has to get inside your cells.
That’s insulin’s job.
Think of insulin as someone knocking on a door, telling your cells to let glucose inside.
Normally, your cells respond, glucose enters, and your blood sugar returns to its usual level.
But with insulin resistance, your cells don’t respond as effectively.
So your pancreas produces more insulin to get the job done.
And more.
For years, your pancreas may work overtime producing extra insulin while your blood sugar remains perfectly normal.
That’s the problem. Your blood sugar can look healthy because your pancreas is working harder to keep it that way.
This isn’t speculation. A 1993 study published in the New England Journal of Medicine found that insulin resistance predicted the development of type 2 diabetes independently of obesity.
Insulin also regulates how your body stores and releases energy. When insulin rises, it temporarily reduces the release of stored fat. Insulin resistance is closely associated with abdominal fat accumulation and metabolic dysfunction, although the relationship works in both directions.
Yet routine diabetes screening focuses on blood glucose and HbA1c, neither of which directly measures insulin sensitivity. Insulin testing is available, but interpreting the results is more complicated, which is one reason it isn’t routinely recommended.
Here’s what deserves far more attention.
Insulin resistance can often improve without weight loss.
Intermittent fasting, including eating within a shorter daily window, may improve insulin sensitivity, although results vary between studies. Replacing ultra-processed foods with whole, minimally processed ingredients can support better metabolic health. Walking after meals and resistance training also help your muscles absorb glucose more efficiently.
These approaches aren’t simply about losing weight. They address how your body processes glucose and responds to insulin.
And that’s what makes the emphasis on detecting diabetes rather than recognizing earlier metabolic problems so frustrating.
If insulin resistance can develop years before diabetes, and we already know ways to improve it, why isn’t identifying and addressing it earlier a greater priority?
Preventing type 2 diabetes should matter just as much as diagnosing it.
2. Thyroid Hormones: When Your Metabolism Slows Down

What if you’re eating the same amount of food, moving just as much as before, but gradually gaining weight?
Your thyroid could be part of the explanation.
This small, butterfly-shaped gland in your neck produces hormones that help control how quickly your body uses energy.
Think of it as part of your body’s energy control system.
Your thyroid produces two main hormones: T4 and T3. T4 is largely converted into T3, the more active hormone that helps your cells use energy.
When thyroid hormone levels become too low, your body uses less energy at rest. You may feel exhausted, unusually cold or constipated, while your weight gradually increases. Some of that weight can also come from fluid retention rather than additional body fat.
But why would your thyroid stop functioning properly in the first place?
One possible explanation is a shortage of essential nutrients.
Your thyroid needs iodine to manufacture hormones, iron to support their production, and selenium to help convert T4 into active T3. Deficiencies can interfere with these processes. But excessive iodine can also disrupt thyroid function, so taking more isn’t necessarily better.
Another major cause is inflammation that damages thyroid tissue.
In Hashimoto’s thyroiditis, immune cells mistakenly attack the cells responsible for producing thyroid hormones. Over time, this can reduce the gland’s ability to function.
But calling it an autoimmune condition describes what’s happening, not what triggered it.
Researchers have investigated several possible contributors, including genetic susceptibility, iodine imbalance, infections and environmental exposures. Changes in gut bacteria and immune regulation are also being studied, although their precise roles remain uncertain.
Some thyroid problems begin after infections or pregnancy, when inflammation temporarily disrupts hormone production. Others develop because of medications. Lithium can interfere with thyroid hormone release, while amiodarone, used for heart rhythm disorders, can cause thyroid dysfunction through several mechanisms.
And there’s another possible influence that’s easy to overlook: the chemicals we encounter in everyday life.
Certain pesticides, PFAS, phthalates and other environmental chemicals have been linked to changes in thyroid hormone activity. Some can interfere with the processes involved in making, transporting or regulating thyroid hormones.
Personal-care products are one potential source of exposure. Shampoo, moisturizer, makeup and perfume may each contain multiple ingredients, while fragrance formulations aren’t always fully disclosed on labels.
In the HERMOSA study, researchers found that switching to personal-care products selected to avoid certain potentially hormone-disrupting chemicals reduced several exposure markers within three days.
That doesn’t establish that these products cause hypothyroidism, but it demonstrates that everyday product choices can meaningfully change chemical exposure.
Food also plays a role in the wider picture. A diet dominated by ultra-processed products may provide fewer essential nutrients and contribute to metabolic problems. However, research hasn’t established that ultra-processed foods directly cause most thyroid disorders.
The important distinction is that thyroid dysfunction doesn’t have one universal root cause.
For one person, an iodine or iron deficiency may be contributing. For another, thyroid tissue may be affected by persistent immune-driven inflammation, medication or a temporary inflammatory condition.
And sometimes, thyroid function is normal, meaning the weight gain has another explanation entirely.
Understanding these differences matters because a thyroid that’s missing essential nutrients, one that’s temporarily inflamed, and one that’s sustained lasting tissue damage aren’t facing the same problem.
If your thyroid is contributing to stubborn weight gain, the real question isn’t simply how to speed up your metabolism. It’s what’s interfering with your thyroid’s ability to function in the first place.
3. Cortisol: How Chronic Stress Changes Your Body

Can stress really make you gain weight, even when you’re not eating more?
Yes, stress can influence how your body uses and stores energy. And the connection goes deeper than emotional eating.
Cortisol is a hormone produced by your adrenal glands, which sit above your kidneys. It helps regulate blood sugar, inflammation, blood pressure and your body’s response to stress.
Think of cortisol as part of your emergency energy system.
When your brain senses danger, cortisol helps make extra fuel available by encouraging your liver to release glucose into your bloodstream. Your body can then use that energy to respond.
That’s exactly what cortisol is supposed to do.
But what happens when the stress never seems to end?
Financial worries, demanding work, relationship problems, chronic pain and disrupted sleep can repeatedly activate your stress-response system.
Over time, this can affect appetite, insulin sensitivity, sleep and the way your body handles energy. It doesn’t mean cortisol stays permanently elevated; prolonged stress can also disturb its normal daily rhythm.
And there’s an important connection to abdominal fat.
In a 2000 Yale University study, researchers found that women with more abdominal fat showed stronger cortisol responses to stress.
But the relationship isn’t necessarily one-way.
Fat tissue contains an enzyme called 11β-HSD1 that can convert inactive cortisone back into active cortisol. Researchers have demonstrated this process in humans, suggesting that cortisol activity within fat tissue can differ from what’s measured in the bloodstream.
In other words, your body’s response to cortisol may matter just as much as the amount circulating in your blood.
Sleep adds another layer.
In a 2024 randomized trial involving 38 women, researchers shortened participants’ sleep by approximately 90 minutes a night for six weeks.
Their insulin sensitivity worsened, even though changes in body fat didn’t explain the result. The effect was particularly pronounced in postmenopausal women.
That’s significant because insulin resistance can develop before blood sugar becomes abnormal, potentially complicating weight regulation.
And sleep isn’t the only factor. Chronic psychological stress can influence food cravings, eating behavior and physical activity, while persistent inflammation and metabolic problems can themselves place additional stress on the body.
So the relationship can work in both directions.
Stress can disrupt the systems involved in weight regulation, while poor sleep and metabolic dysfunction may make it harder for the body to recover.
This doesn’t mean every person with abdominal weight gain has high cortisol. Persistently excessive cortisol, as seen in Cushing syndrome, is a distinct medical condition that can cause significant changes in fat distribution and muscle strength.
But ordinary chronic stress doesn’t have to become a diagnosable cortisol disorder to affect your metabolism.
The real question isn’t simply whether your cortisol is high. It’s whether prolonged stress and inadequate recovery are interfering with the hormonal systems that regulate your energy, appetite and body fat.
4. Leptin Resistance: When Your Brain Stops Listening

How can someone have thousands of calories stored as body fat and still feel hungry shortly after eating?
The answer involves something most people have probably never heard of: leptin.
Leptin is a hormone produced mainly by your fat cells. Its job is to communicate with your brain about how much energy your body has stored.
Think of it as a fuel gauge.
When your fat stores are plentiful, leptin levels are generally higher. This helps tell your brain that energy is available. When fat stores shrink, leptin levels fall, signaling that your energy reserves are becoming smaller.
But here’s where things get interesting.
People carrying excess body fat often have plenty of leptin circulating in their blood. You might expect that to make them feel less hungry.
Yet that isn’t necessarily what happens.
Researchers have found that in obesity, the brain may become less responsive to leptin’s signals. This is known as leptin resistance.
In simple terms, the fuel gauge is showing that energy is available, but the brain isn’t responding to the message as expected.
Scientists are still investigating exactly why this happens. Inflammation, changes in brain signaling, and impaired leptin transport have all been studied, but there isn’t one established explanation that applies to everyone.
Here’s something else you may never have been told: losing weight can actually make your body fight harder to regain it.
When you lose body fat, leptin levels fall. Your brain can interpret that change as a warning that energy reserves are running low.
The response can be powerful.
You become hungrier. Food may seem more appealing. Your body may also reduce its energy expenditure, meaning it burns fewer calories than expected after accounting for its smaller size.
And these changes don’t necessarily disappear when you stop dieting.
In a landmark 2011 study published in the New England Journal of Medicine, researchers followed 50 adults with overweight or obesity through a weight-loss program. After participants lost an average of 13.5% of their body weight, researchers measured substantial changes in several appetite-regulating hormones, including leptin and ghrelin.
A year later, many of these hormonal changes remained, even though participants had regained some weight. They also reported feeling hungrier than before losing weight.
Think about what that means.
Someone can successfully lose weight, maintain healthier eating habits, and still experience stronger biological pressure to eat than they did before dieting.
Yet the usual explanation for regaining weight is often that they stopped trying hard enough.
The research tells a more complicated story.
It doesn’t mean weight regain is inevitable, or that leptin resistance explains every case of stubborn weight gain. It means appetite and body weight are regulated by biological systems that can actively respond to weight loss.
And despite the supplements and diets marketed as ways to reset leptin, there is currently no established treatment that simply switches common leptin resistance off. Routine leptin testing is rarely useful for diagnosing ordinary weight-management difficulties.
So if you’ve repeatedly lost weight only to regain it, or find yourself unusually hungry after dieting, understanding leptin changes the conversation.
Your body isn’t simply responding to how much food you eat. It’s also responding to how much energy it believes you have left.
And sometimes, those biological signals can make maintaining weight loss considerably harder than losing it in the first place.
5. Estrogen: Why Weight Changes During Perimenopause

Why do so many women start gaining weight around their stomach in their 40s and 50s, even when their eating habits haven’t changed?
The answer may have less to do with willpower and more to do with what happens to estrogen during perimenopause.
Estrogen is often described as a reproductive hormone, but its influence extends far beyond menstruation. It also affects the brain, muscles, bones, insulin sensitivity, and how fat is distributed throughout your body.
And this is where things become particularly interesting.
Before menopause, women generally store a greater proportion of their body fat around the hips and thighs. This is known as subcutaneous fat, meaning fat stored beneath the skin.
As estrogen declines during the menopausal transition, fat distribution often changes. More fat begins accumulating around the abdomen, including deeper visceral fat surrounding internal organs.
Here’s what many women aren’t told: your body composition can change even when the number on the scale barely moves.
You might lose muscle, gain abdominal fat, and find that your clothes fit differently without experiencing a dramatic increase in total body weight.
This isn’t simply an assumption based on women getting older.
Researchers in the United States followed women through midlife in the Study of Women’s Health Across the Nation (SWAN). An analysis published in JCI Insight in 2019 examined changes in body composition around the final menstrual period.
The researchers found that fat gain accelerated and lean mass declined during the menopausal transition. After menopause, the rates of change slowed.
Importantly, body weight alone didn’t reveal the full extent of these changes.
That distinction matters because muscle tissue plays an important role in glucose regulation. When you lose muscle, you may also lose some of the tissue responsible for taking up glucose from your bloodstream.
Meanwhile, increasing visceral fat is associated with insulin resistance and other metabolic changes.
So estrogen decline may influence more than where fat accumulates. It can contribute to changes in the metabolic environment that make weight management more challenging.
But estrogen isn’t the only factor.
Sleep disturbances, hot flashes, declining physical activity, age-related muscle loss, and changes in appetite can all contribute. Separating the effects of menopause from aging is difficult, which is why not every pound gained during midlife can be blamed on hormones.
There’s another important detail about perimenopause.
Estrogen doesn’t simply decline in a straight line.
During perimenopause, hormone levels can fluctuate considerably. Estrogen may be high at one point and much lower at another, while progesterone production often becomes less consistent as ovulation becomes irregular.
This helps explain why symptoms can appear unpredictable.
One month, you may sleep normally. The next, you’re waking repeatedly, experiencing night sweats, or noticing changes in your menstrual cycle.
And disrupted sleep can influence hunger, energy levels, and eating behavior, adding another layer to the changes already taking place.
So shouldn’t doctors simply measure estrogen?
Unfortunately, one blood test rarely gives a useful picture of perimenopause.
Estradiol and follicle-stimulating hormone (FSH) can fluctuate substantially from day to day. A result within the laboratory’s normal range doesn’t necessarily rule out perimenopause.
For women over 45 with typical symptoms and menstrual changes, clinicians generally diagnose perimenopause from the clinical history rather than relying on routine hormone testing.
This doesn’t mean symptoms should be dismissed. It means a single hormone result may not capture what is happening across an entire menstrual cycle.
And what about hormone replacement therapy?
Menopausal hormone therapy can be effective for hot flashes, night sweats, and other menopausal symptoms. Some evidence suggests it may modestly reduce abdominal fat accumulation, but it isn’t recommended as a weight-loss treatment.
Treatment decisions should consider symptoms, medical history, age, and individual risks.
The bigger question is whether your weight gain reflects an increase in total body fat, a shift towards abdominal fat, declining muscle mass, or a combination of all three.
Those differences matter.
If you’re in your 40s or 50s and noticing a thicker waist, changing periods, disturbed sleep, or a different response to your usual eating habits, perimenopause deserves consideration.
Waist circumference, blood pressure, blood glucose, cholesterol, and changes in muscle strength may reveal more about your metabolic health than the bathroom scale alone.
Because during perimenopause, the problem isn’t always that you’re gaining more weight. Sometimes it’s that your body is storing fat differently while gradually losing the muscle that helps regulate your metabolism.
6. Testosterone: When Hormonal Imbalances Affect Weight

Testosterone is usually associated with men, but women produce it too. And when testosterone levels become unusually high, the effects can extend far beyond reproductive health.
One of the clearest examples is polycystic ovary syndrome (PCOS), a hormonal condition that affects an estimated 10–13% of women of reproductive age worldwide.
PCOS is often associated with irregular periods, acne, increased facial or body hair, and difficulty becoming pregnant. But there’s another connection that deserves attention: insulin resistance.
Here’s what many women don’t realize: insulin and testosterone can influence each other.
Remember how insulin resistance can force your pancreas to produce more insulin to keep blood sugar under control?
In women with PCOS, elevated insulin can also stimulate the ovaries to produce more androgens, including testosterone. It can reduce the liver’s production of sex hormone-binding globulin (SHBG), a protein that binds testosterone in the bloodstream.
When SHBG falls, more testosterone may remain available to act on tissues.
This can contribute to symptoms such as acne, unwanted facial hair, and irregular ovulation.
But the relationship doesn’t stop there.
Excess androgen activity may also contribute to abdominal fat accumulation and metabolic dysfunction. In turn, increasing abdominal fat can worsen insulin resistance, potentially reinforcing the hormonal disturbance.
Think about what that means.
A woman might notice increasing waist measurements, irregular periods, and stubborn weight gain without realizing these symptoms could be connected.
And because PCOS is often discussed primarily as a fertility condition, its metabolic implications may receive less attention than they deserve.
Researchers have been investigating this connection for decades.
In a landmark American study published in Diabetes in 1989, researchers examined insulin sensitivity in women with PCOS and found significant insulin resistance, including among women who were not obese.
This was an important finding because it demonstrated that insulin resistance in PCOS wasn’t simply a consequence of carrying excess body weight.
You can have PCOS-related insulin resistance without being overweight.
That also means weight gain isn’t required for PCOS to exist.
Some women with PCOS have a higher body weight, while others remain lean. Not everyone with PCOS has elevated testosterone on a blood test, and not everyone with elevated testosterone has PCOS.
So how do doctors investigate it?
PCOS is diagnosed using a combination of findings rather than a single testosterone result. In adults, the diagnosis generally requires at least two of three features: irregular or absent ovulation, clinical or biochemical evidence of excess androgens, and polycystic ovarian morphology on ultrasound or an appropriately interpreted anti-Müllerian hormone (AMH) test.
Other conditions that can produce similar symptoms must first be excluded.
This is particularly important because the name polycystic ovary syndrome can be misleading. You don’t necessarily need ovarian cysts to have PCOS.
Blood tests may include total and free testosterone or a calculated measure of free testosterone, along with tests to rule out other hormonal conditions.
And because PCOS is associated with a higher risk of impaired glucose tolerance and type 2 diabetes, metabolic screening matters too.
The 2023 International Evidence-Based Guideline for PCOS recommends a 75-gram oral glucose tolerance test as the most accurate way to assess glycemic status in women with PCOS, regardless of BMI.
Unlike a fasting glucose test, which provides a single measurement, this test examines how your blood sugar responds after drinking a measured amount of glucose.
It still doesn’t directly measure insulin resistance, but it can reveal glucose regulation problems that fasting tests may miss.
There’s another distinction worth understanding.
Testosterone isn’t automatically a problem for women.
Normal androgen levels contribute to reproductive function and other physiological processes. The concern is excessive androgen activity or an underlying condition disrupting hormonal regulation.
And testosterone levels normally decline with age. This doesn’t mean every woman gaining weight during midlife has a testosterone deficiency, or that testosterone treatment is an appropriate weight-loss solution.
In fact, testosterone therapy is not recommended for treating weight gain in women.
If you’re experiencing unexplained weight changes alongside irregular periods, persistent acne, increased facial hair, or scalp hair thinning, discussing possible androgen excess and PCOS with your doctor is reasonable.
Rapidly developing symptoms, such as a deepening voice or sudden severe facial hair growth, require prompt medical assessment because they can occasionally indicate a more serious cause of androgen excess.
The important lesson is that weight gain, insulin resistance, and reproductive hormones don’t always operate independently.
Sometimes, several seemingly unrelated symptoms are different signs of the same underlying hormonal disturbance.
7. Ghrelin: Why Weight Loss Makes You Hungrier
Have you ever noticed that the longer you diet, the harder it becomes to ignore food?
You might start a weight-loss plan feeling satisfied with smaller portions. But several weeks later, you’re thinking about your next meal before you’ve finished the one in front of you.
That’s not necessarily a lack of discipline. Your body has a hormone specifically involved in making you hungry.
It’s called ghrelin.
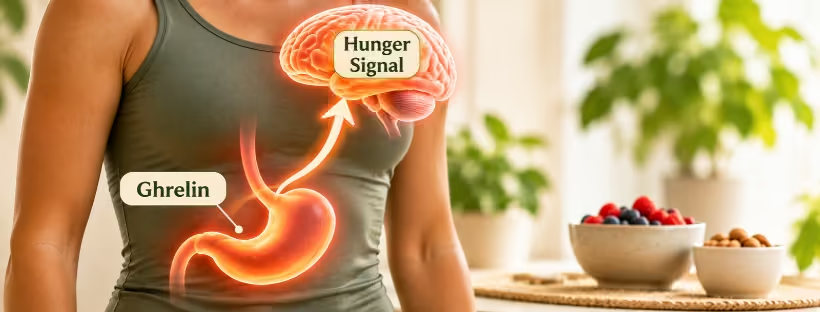
Ghrelin is produced mainly in your stomach. It travels through your bloodstream and communicates with areas of your brain involved in appetite and energy regulation.
Think of it as one of your body’s hunger signals.
Ghrelin typically rises before meals and falls after eating. When levels increase, your brain receives a message encouraging you to find food.
But ghrelin does more than remind you that lunchtime is approaching. It also helps your body respond to changes in energy availability.
And that’s where weight loss becomes complicated.
Here’s something most diets never explain: losing weight can make the hormones that drive hunger work harder against you.
In a 2002 study published in the New England Journal of Medicine, researchers at the University of Washington examined circulating ghrelin levels in people who lost weight through dietary restriction.
They found that ghrelin increased after diet-induced weight loss.
The researchers also observed a striking difference in people who had undergone gastric bypass surgery: their ghrelin levels were markedly lower than expected.
The study was relatively small, and subsequent research has shown that ghrelin responses vary depending on the type of bariatric surgery. Nevertheless, it helped establish that weight loss and the method used to achieve it can influence hunger-related hormonal signals.
Now think about what happens during a typical diet.
You’re eating less, so your body receives less energy. As weight falls, several physiological systems begin adjusting to protect against further energy loss.
Ghrelin may increase, making food more appealing and hunger more difficult to ignore.
Meanwhile, leptin, the hormone we discussed earlier, generally falls as body fat decreases.
These changes can work together: one signal encourages you to eat, while another provides less of the usual information that your energy stores are sufficient.
Your body may be actively encouraging you to replace the weight you’ve lost.
This helps explain why maintaining weight loss can feel harder than losing it initially.
But there’s another important distinction.
Ghrelin isn’t simply a hormone that makes people overweight.
In fact, fasting ghrelin levels are often lower in people with obesity than in lean individuals. The relationship between ghrelin, appetite, and body weight is far more complicated than assuming that more hunger always means more ghrelin.
The timing of meals, sleep, weight changes, and the body’s response to food all influence hunger regulation.
And ghrelin isn’t acting alone.
Your intestines also release hormones such as GLP-1 and PYY after eating. These help communicate fullness to your brain and influence how quickly food moves through your digestive system.
This is one reason two meals containing the same number of calories may leave you feeling very different afterward.
Protein, fiber, food structure, and the extent of processing can influence digestion and fullness. Liquid calories, for example, often produce a different satiety response from solid foods.
Researchers at the National Institutes of Health demonstrated how important food composition can be in a controlled 2019 study published in Cell Metabolism.
Twenty adults spent two weeks eating an ultra-processed diet and two weeks eating an unprocessed diet. The meals were matched for several nutritional characteristics, and participants could eat as much or as little as they wanted.
During the ultra-processed diet, participants consumed approximately 500 additional calories per day and gained weight. During the unprocessed diet, they ate less and lost weight.
Interestingly, the researchers also measured appetite-related hormones. The unprocessed diet was associated with lower ghrelin levels and higher PYY levels compared with the ultra-processed diet.
The study doesn’t prove that ghrelin caused the differences in food intake. Eating speed, energy density, food texture, and other factors may also have contributed.
But it challenges the idea that appetite is simply a conscious decision.
What you eat can influence how much you want to eat next.
Beyond appetite and calorie intake, ultra-processed foods may also affect gut bacteria, intestinal health, and metabolic regulation, raising questions about their wider effects on the body.
And what about testing ghrelin?
Unlike blood glucose or thyroid hormones, ghrelin isn’t routinely measured when someone struggles to lose weight. Levels fluctuate with meals and other physiological conditions, and there is no established clinical cutoff that diagnoses ordinary weight-management difficulties.
So a commercial hormone panel promising to identify your hunger problem from a single ghrelin measurement should be approached cautiously.
What matters more is understanding why persistent hunger may develop.
If you’ve been repeatedly restricting calories, losing weight, and regaining it, your appetite may be responding to biological adaptations rather than a sudden failure of self-control.
Adequate sleep, satisfying meals containing protein and fiber, and avoiding unnecessarily severe calorie restriction can help support appetite management. But these measures don’t completely eliminate the body’s response to weight loss.
Because hunger isn’t simply an empty stomach asking for food. It’s part of a hormonal system that monitors energy availability and responds when your body begins losing its reserves.
And understanding that system is essential if you want to stop treating every unsuccessful diet as a personal failure.
Gaining Weight Despite Normal Blood Tests?

Your blood tests are normal, but your weight keeps increasing. Does that mean everything is functioning as it should?
Not necessarily. Routine blood tests don’t measure every aspect of hormonal or metabolic health. But unexplained weight gain doesn’t automatically mean you have a hormonal disorder either.
The symptoms accompanying your weight changes may offer clues about what’s happening beneath the surface.
| What You’re Experiencing | What May Be Contributing |
|---|---|
| Abdominal weight gain, particularly with elevated triglycerides or blood pressure | Insulin resistance and metabolic changes |
| Weight gain with fatigue, constipation, dry skin, or feeling unusually cold | Reduced thyroid function |
| Increasing waist size, changing periods, and disrupted sleep during midlife | Perimenopause and changes in fat distribution |
| Weight gain alongside acne, facial hair, or irregular periods | Androgen excess or PCOS |
| Rapid abdominal weight gain with easy bruising, purple stretch marks, or muscle weakness | Excessive cortisol production, including Cushing syndrome |
| Persistent hunger and weight regain after dieting | Changes in leptin, ghrelin, and energy expenditure |
These patterns aren’t diagnoses, but understanding them can help you recognize when your body may need additional support.
The encouraging part is that many of the systems involved in weight regulation respond to everyday habits.
Here’s where to start:
- Eat real, minimally processed food. Build meals around quality protein, vegetables, fruit, and naturally fiber-rich foods. These help support blood sugar regulation and provide nutrients your body needs for normal hormone production.
- Build muscle. Resistance training improves insulin sensitivity and helps preserve metabolically active muscle, particularly important during perimenopause and beyond.
- Protect your sleep. Consistent, sufficient sleep supports appetite regulation, glucose metabolism, and your natural cortisol rhythm.
- Move after meals. Even a short walk encourages your muscles to use circulating glucose, helping improve blood sugar control.
- Stop fighting your body with extreme diets. Severe calorie restriction can increase hunger, lower energy expenditure, and make maintaining weight loss harder.
- Make recovery part of your routine. Chronic stress can influence sleep, appetite, and eating behavior. Mindfulness, time outdoors, and regular relaxation can help support a healthier stress response.
None of these habits requires an expensive hormone panel, detox program, or supplement marketed as a hormonal reset.
However, lifestyle changes cannot correct every underlying condition. Persistent symptoms deserve proper investigation, and rapid weight gain accompanied by easy bruising, significant muscle weakness, or unexplained swelling should not be dismissed.
Your body already has sophisticated systems for regulating hormones, appetite, and energy. Supporting those systems through consistent daily habits is a meaningful starting point—not because every hormonal problem can be fixed naturally, but because your everyday choices can influence how well many of these systems function.
Final Thoughts: When Weight Gain Is More Than Calories

If you’ve been eating carefully, staying active, and still struggling with your weight, it’s worth asking a different question: what else could be influencing how your body regulates energy?
As we’ve explored, hormones don’t work independently. Insulin helps regulate blood sugar and energy storage. Leptin and ghrelin influence hunger and fullness. Thyroid hormones affect energy expenditure, while cortisol, estrogen, and testosterone can influence metabolism, appetite, and fat distribution.
Changes in one system can affect another.
But not every difficulty losing weight is caused by a hormonal disorder. Aging, medications, sleep, body composition, and metabolic adaptations to previous weight loss can all play a role. And some hormonal changes are consequences of weight gain rather than its original cause.
The important distinction is between normal hormonal responses, metabolic dysfunction, and conditions that require medical treatment.
A normal blood sugar result doesn’t directly measure insulin sensitivity. A normal thyroid test doesn’t explain every symptom. And a single estrogen or cortisol measurement rarely tells the whole story.
If your weight has changed unexpectedly, especially alongside fatigue, irregular periods, persistent hunger, or increasing abdominal fat, ask your healthcare professional to investigate the symptoms together rather than focusing on the scale alone.
You don’t need an expensive hormone panel or another supplement promising to balance everything. You need to understand which tests are meaningful, what they actually measure, and whether your symptoms suggest an underlying condition.
Weight management involves more than deciding how much to eat. Understanding the biology behind your body’s responses is a better starting point than assuming every setback comes down to willpower.
